Ask before assisting
Explain the next task and allow time for the person to respond. Avoid several adults giving different instructions or rushing a movement because the household is busy.

Mobility & transfers · Dubai
Getting from a chair to the bathroom, reaching the dining table or stepping outside can shape an older person’s independence. We start with the actual movement task, existing advice and the home environment, then agree practical support and any separate clinical assessment needed.

 Clinical author assignmentDr Toqa IbrahimTwo clinical perspectivesProfiles & DHA directory links Guidance with sourcesExplore the references
Older-adult mobility and transfer support
Tell us which transfers or everyday journeys need help, what equipment is already prescribed and whether there have been falls or recent changes. A caregiver can support an agreed practical plan; a nurse or rehabilitation professional may be needed for clinical assessment or specific care. Staffing and equipment must fit the actual task.
Understand the care

Mobility support is often about familiar tasks: standing from a favourite chair, reaching the toilet or moving between rooms. The aim is to understand what the person can do, what they want to keep doing and where help is needed. Taking over every movement can be as unhelpful as expecting someone to manage an unsafe task alone.
The arrangement should follow an appropriate assessment and current clinical advice. A change in balance, strength, pain or confidence may need review rather than simply more assistance. Practical caregiving, nursing and physiotherapy have different contributions; the correct combination depends on the person’s needs, not age alone.
The home matters too. Space, access, lighting, furniture and prescribed equipment can affect what is workable. Describe the actual environment before care begins. The plan should make staffing, transfer methods and escalation clear without teaching a universal lifting technique through a website.
Read the clinical sourcesSupport for the caregiver
Support should make everyday life more workable while respecting the older person’s preferences and remaining abilities.

Explain the next task and allow time for the person to respond. Avoid several adults giving different instructions or rushing a movement because the household is busy.
Make sure relevant instructions reach everyone helping. If a transfer feels different or harder, pause and seek the appropriate advice rather than adding force or improvising a technique.
Report what happened, where and when. A specific change in getting up or walking is more useful to a clinician than a broad label such as becoming frail.
The rhythm of a day
Select priorities for the care discussion. These choices do not assess transfer safety or prescribe an exercise.
Describe the chair or bed, the help currently required and any pain or uncertainty. The team needs the actual task, not only a general statement that mobility is reduced.
Explain the route, doorway space and existing aids. Privacy and timing matter alongside physical assistance, and any unsafe setup may need professional assessment.
Share the current walking aid and relevant clinical advice. A caregiver should not replace a prescribed aid or introduce a new method without appropriate guidance.
Describe when the fall occurred and what assessment has already happened. New injury or a change in function may require medical review before routine support is arranged.
Explain whether a physiotherapist has provided a plan. Practical support can follow agreed instructions, but it is not a substitute for rehabilitation assessment or progression.
Ask the older person what feels difficult and what matters to them. Respect their pace and choices rather than making every decision through relatives.
Your discussion list
Choose the points you would like to discuss.
The first assessment
A safe practical arrangement requires more detail than selecting a number of hours.
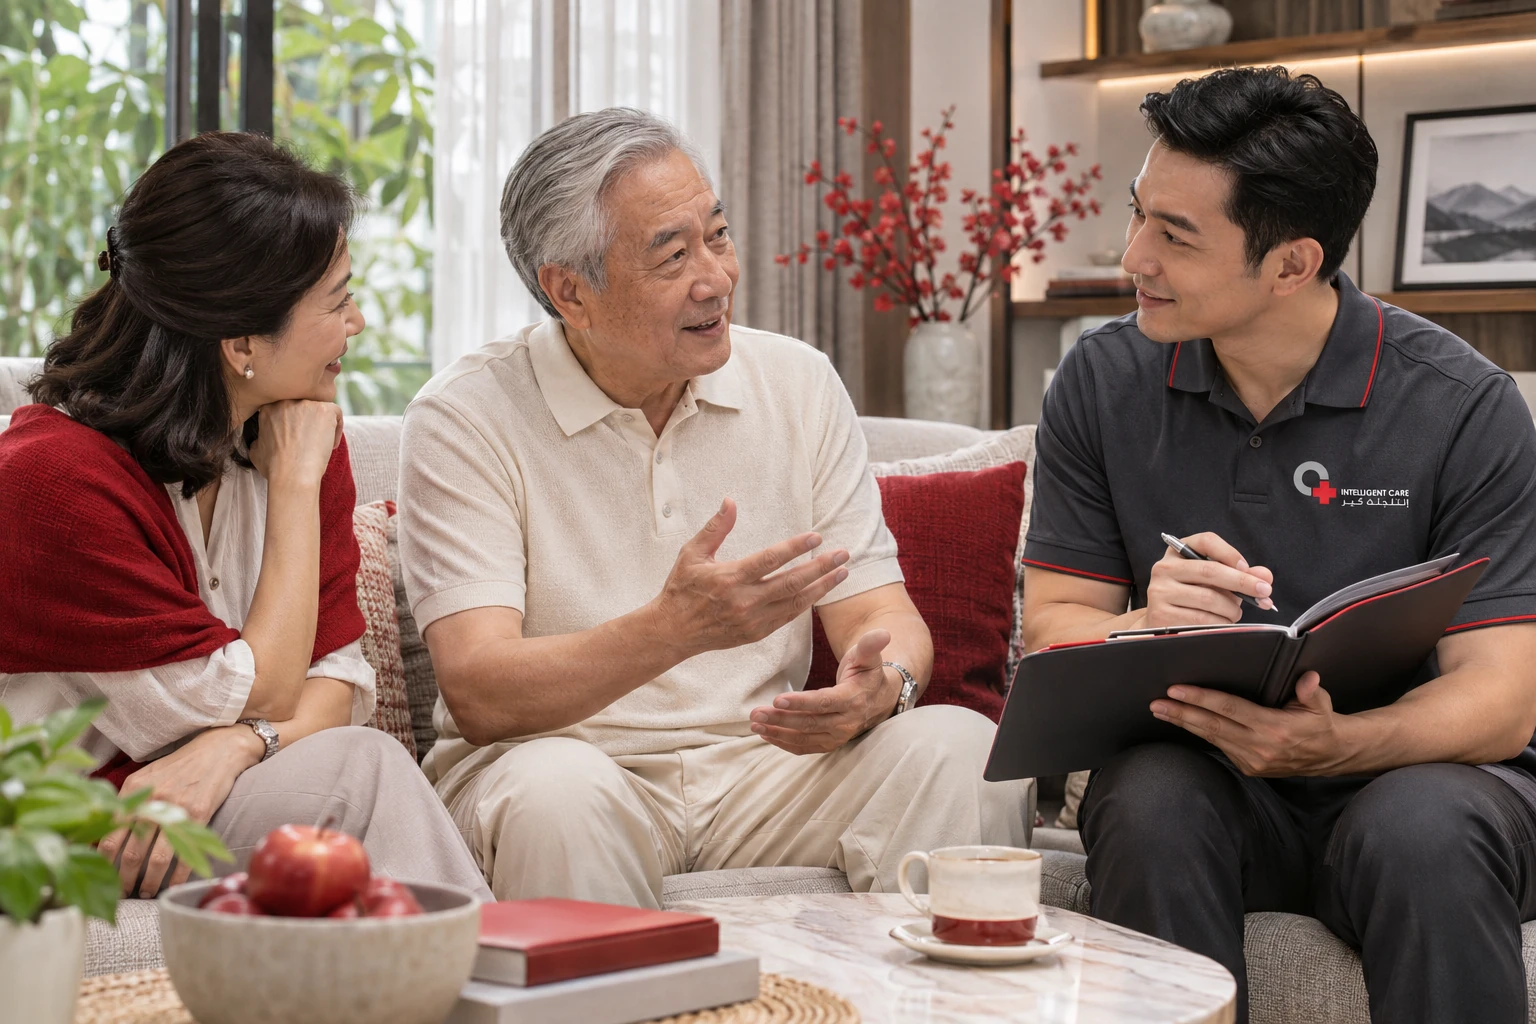
THE CARE CONVERSATION01—04
Discuss current ability, recent changes, falls, pain, restrictions and existing professional advice. Identify whether a clinical review is needed before support starts.
Explain the rooms, furniture, access and equipment involved in the everyday movements. Share practical constraints so the proposed arrangement reflects the actual home.
Agree appropriate staffing, equipment and professional responsibilities. Do not assume a caregiver can improvise a transfer or that every task is suitable for one person.
Reconsider the arrangement when ability, confidence or clinical instructions change. A plan that was suitable last month may not be suitable after an illness or fall.
Before care arrives
Keep the practical details and existing clinical advice together.

A personal reminder list.
Nothing is sent or saved.
What the care involves
The person’s assessment and preferences guide the practical plan.
| Need | Appropriate contribution | Boundary |
|---|---|---|
| 01Daily movement assistance | A caregiver supports the agreed routine and method within the confirmed scope. | No unassessed lifting technique or guarantee that falls cannot happen. |
| 02Clinical nursing needs | A nurse contributes when the person’s condition or care tasks require nursing expertise. | Nursing does not automatically replace rehabilitation assessment. |
| 03Rehabilitation | A physiotherapist assesses movement and develops or reviews the relevant programme. | Exercises and progression are individualized, not selected by a caregiver from a generic list. |
| 04Equipment and home setup | The team clarifies prescribed aids and practical requirements. | Equipment selection, fitting and training need the appropriate professional input. |
The care pathway
The sequence follows assessed needs, not a promised recovery timetable.
Describe movement ability, restrictions and the practical goal.
Confirm staffing, equipment and the home arrangement.
Follow the agreed method and respect the person’s pace.
Review after a fall, illness or meaningful change.
Explore a stage to bring it into focus. Every stage stays visible.
People and responsibilities
Age alone does not determine the professional you need. Start with the person’s priorities, the practical help required and any clinical task in the existing plan.
Supports agreed everyday activities and reports relevant changes. A caregiver does not diagnose illness, independently alter medicines or replace a nurse for clinical procedures.
Assesses and delivers nursing care within the agreed clinical scope, instructions and professional responsibilities. Explain specialist procedures or equipment before booking so competence and supplies can be confirmed.
Make the relevant clinical decisions and guide specialist treatment, rehabilitation or nutrition where needed. Home support should connect with that advice rather than replace it by default.
Coordinate practical arrangements and agreed communication. Involve the older person directly, respect their choices and identify who may receive information, rather than assuming every relative has the same authority.
Read the real team profiles and their professional-directory references. Your assigned professional and the scope of care are confirmed through the care arrangement.
Meet our clinical teamContinuity of care
A mobility arrangement should change when the person or the environment changes.
Ask whether the assistance feels respectful and manageable, and whether a task has become more difficult.
Check that everyone follows the current instructions and that equipment remains appropriate and usable.
Raise new pain, weakness, dizziness or a fall with the relevant professional rather than treating it only as a staffing problem.
Review the everyday activity that matters to the person and whether rehabilitation or a different support level is needed.
When to seek medical help
Routine mobility support is not a substitute for assessment after a potentially serious fall or new neurological symptom.
Immediate medical attention
Prompt clinical assessment
Practical arrangements
Choose nursing or caregiving for the agreed duties, then the short- or long-term period that fits. You can compare the published prices for standard plans and add your chosen period to the care bag. Custom and annual arrangements begin with a care enquiry so the team can clarify the duties, schedule and price.
Most families begin by arranging the support they need directly. The plan should make the professional role, coverage period, duties and additional services clear. A monthly 24-hour arrangement is coordinated coverage, not one person working continuously without rest.
Intelligent Care accepts CDA payment for approved arrangements. Share the approval so the team can confirm its scope before care begins; agreed care normally proceeds on credit and CDA settles later. Approval is not automatic, and CDA is the payer in this pathway, not the clinical regulator.
An earliest-available request remains pending agreement and does not collect payment. Use the custom route for a complex schedule or uncertain clinical scope. Insurance, where relevant, is checked separately against the policy and any authorization requirements.
Your questions
No. The required assistance depends on the person, task, equipment and assessment. Describe the current method and any restrictions before booking. Staffing must be confirmed rather than assuming one person can safely lift or move someone in every situation.
No. Practical movement assistance and physiotherapy are different services. A physiotherapist assesses function and develops or reviews rehabilitation where appropriate. A caregiver can support an agreed routine within scope but does not independently prescribe exercises or progression.
Explain what happened and whether the person has been medically assessed. A potentially serious injury, inability to get up or new neurological signs requires urgent care. Once clinical needs are clear, practical support can be discussed around the current advice.
Do not assume equipment is included. Explain what is already prescribed and what may be needed. Selection, fitting, training, supply and maintenance responsibilities must be confirmed with the appropriate professionals before the task is undertaken.
The plan should respect the person’s abilities and preferences. Support is tailored to the assessed task, not automatically full assistance for every movement. Ask the relevant professional how independence can be supported safely in the individual situation.
Describe the practical and clinical needs separately. The team can discuss appropriate roles and arrangements, but one standard plan should not imply every professional service is bundled together. Each task and responsibility needs to be clear.
For an approved CDA-supported arrangement, share the authorization so the team can confirm scope. Agreed care normally proceeds on credit and CDA settles later. Approval is not automatic and does not determine whether a particular transfer method or clinical task is safe.
Start with the actual mobility task, current advice and equipment. Choose a standard plan only when the duties fit its scope, or use a custom enquiry for complex transfers or uncertain requirements. The person’s safety and appropriate role come before the booking period.
Expertise with a name
Explore the named clinical profiles, their professional roles and their Dubai Health Authority directory records.
Author assignment
General Practitioner
Dr Toqa Ibrahim is a DHA-licensed General Practitioner with Alpha Intelligent Care Home Healthcare Center. Her clinical profile brings the general-practice perspective into our approach to care at home.

Review assignment
Specialist Clinical Pathology
Dr Joyce Jose is a DHA-licensed Specialist in Clinical Pathology at Intel Lab. Her public professional record includes pathology practice in the UAE and earlier experience as a professor at Gulf Medical University.
Professional registration describes each clinician’s role. The clinical assessment and the person responsible for your care are confirmed separately.
More care guides



The wider picture
Explore related support, or speak to us about combining services into one plan.
About this guide
General information supports the care conversation; your own assessment determines the plan. Company service information and independent clinical guidance are listed separately below.
Care that comes to you
Across Dubai.
Abu Dhabi — coming soon.


